Real patients being treated with DUPIXENT. Individual results may vary.
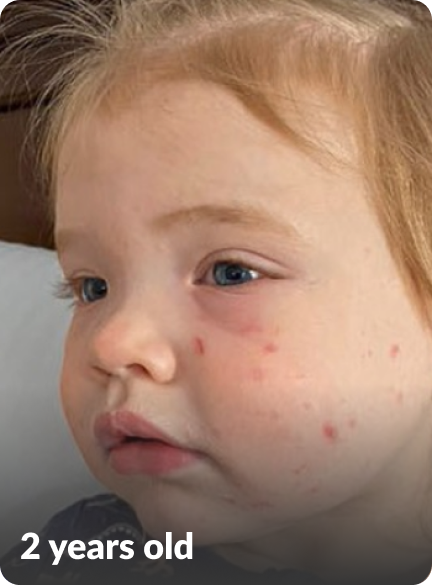
“She was so young and didn’t understand that she shouldn’t be scratching.”
—Lila’s mom
Needed more options for relief
- Before she was barely old enough to crawl, Lila began presenting with signs and symptoms of moderate AD
- What started as minor lesions rapidly developed into worsening skin lesions, primarily on her face
- Lila’s skin was so itchy, resulting in uncontrollable scratching on the affected areas
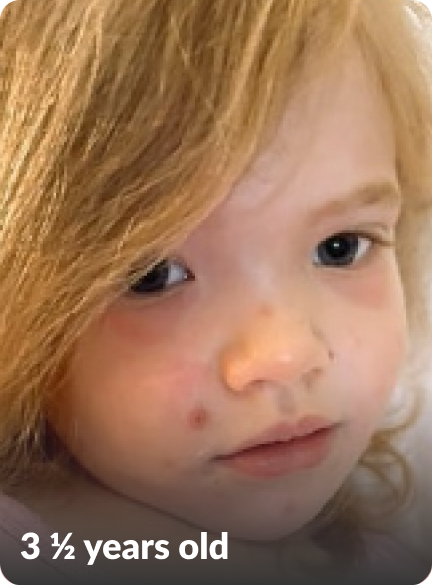
“Many times, it felt like we would just get things under control and then she would have another flare. Some treatments would initially work, but then they would stop working for her.”
—Lila’s mom
Stuck in a cycle of flare, treat, repeat
- Warmer weather seemed to trigger Lila’s flares
- Being outdoors during the summertime was difficult for Lila and her parents
- Application of topical Rxs was difficult, as she would often try to rub them off
- After trying multiple topical Rxs, Lila was finally referred to a specialist
- Her mother grew concerned about how other children and parents might react to her condition

“DUPIXENT has made a difference. If I could go back in time and start Lila’s treatment earlier, I would!”
—Lila’s mom
Finding hope with DUPIXENT
- After partnering with a specialist, Lila’s parents decided to try DUPIXENT when she was 4 years old
- Her parents began to notice improvements in her skin lesions, and her itch also improved
- Her disease is now under control
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia. The long-term safety profile of DUPIXENT ± TCS observed in infants to preschoolers was consistent with that seen in adults, adolescents and children with atopic dermatitis. In AD-1434, hand-foot-and-mouth disease and skin papilloma (incidence ≥2%) was reported in infants to preschoolers. These cases did not lead to study drug discontinuation.1
“She was so young and didn’t understand that she shouldn’t be scratching.”
—Lila’s mom
Needed more options for relief
- Before she was barely old enough to crawl, Lila began presenting with signs and symptoms of moderate AD
- What started as minor lesions rapidly developed into worsening skin lesions, primarily on her face
- Lila’s skin was so itchy, resulting in uncontrollable scratching on the affected areas
“Many times, it felt like we would just get things under control and then she would have another flare. Some treatments would initially work, but then they would stop working for her.”
—Lila’s mom
Stuck in a cycle of flare, treat, repeat
- Warmer weather seemed to trigger Lila’s flares
- Being outdoors during the summertime was difficult for Lila and her parents
- Application of topical Rxs was difficult, as she would often try to rub them off
- After trying multiple topical Rxs, Lila was finally referred to a specialist
- Her mother grew concerned about how other children and parents might react to her condition
“DUPIXENT has made a difference. If I could go back in time and start Lila’s treatment earlier, I would!”
—Lila’s mom
Finding hope with DUPIXENT
- After partnering with a specialist, Lila’s parents decided to try DUPIXENT when she was 4 years old
- Her parents began to notice improvements in her skin lesions, and her itch also improved
- Her disease is now under control
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia. The long-term safety profile of DUPIXENT ± TCS observed in infants to preschoolers was consistent with that seen in adults, adolescents and children with atopic dermatitis. In AD-1434, hand-foot-and-mouth disease and skin papilloma (incidence ≥2%) was reported in infants to preschoolers. These cases did not lead to study drug discontinuation.1
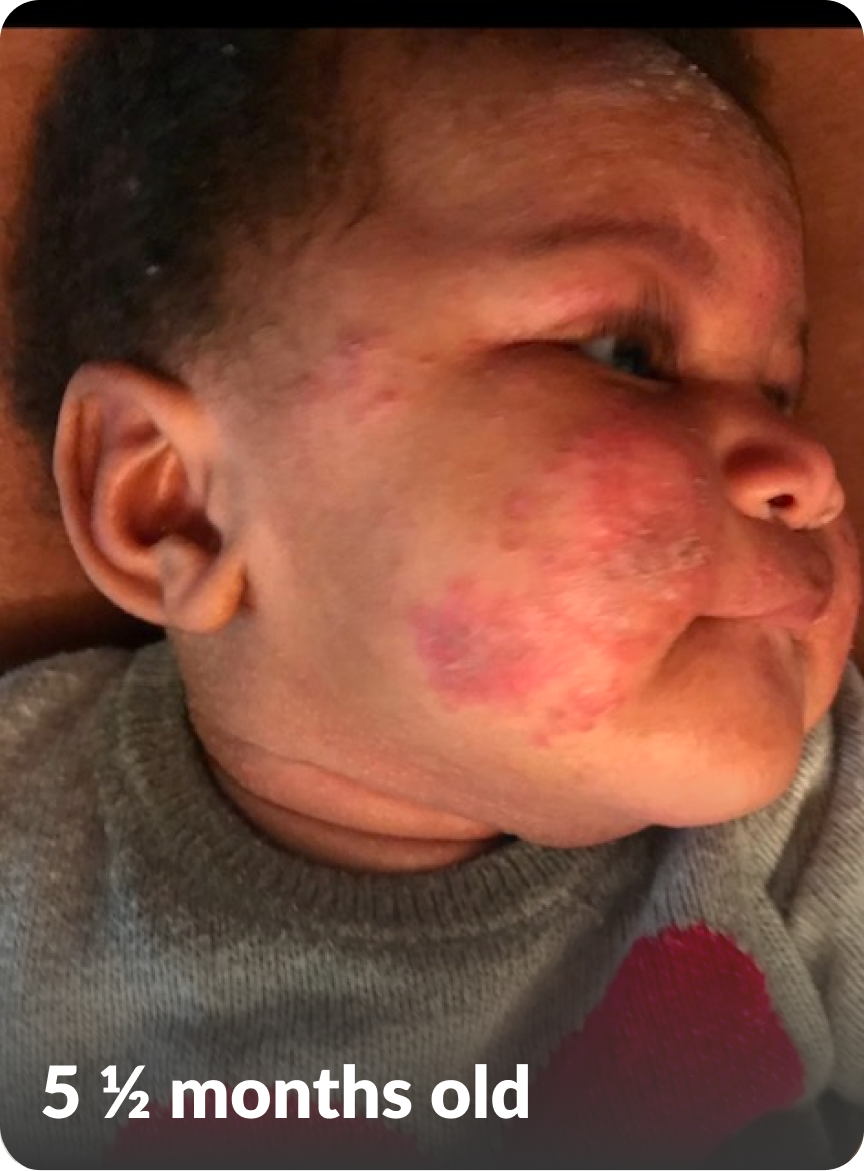
“Looking back on early pictures, her face looked so irritated.”
—Bailey’s mom
Signs and symptoms began in the first year of life
- Red, dry, patchy rashes on Bailey’s cheeks were first thought to be caused by the weather
- Intractable itching and oozing lesions spread to her scalp, arms, neck, and torso
- A diagnosis of severe AD was confirmed at 7 months of age
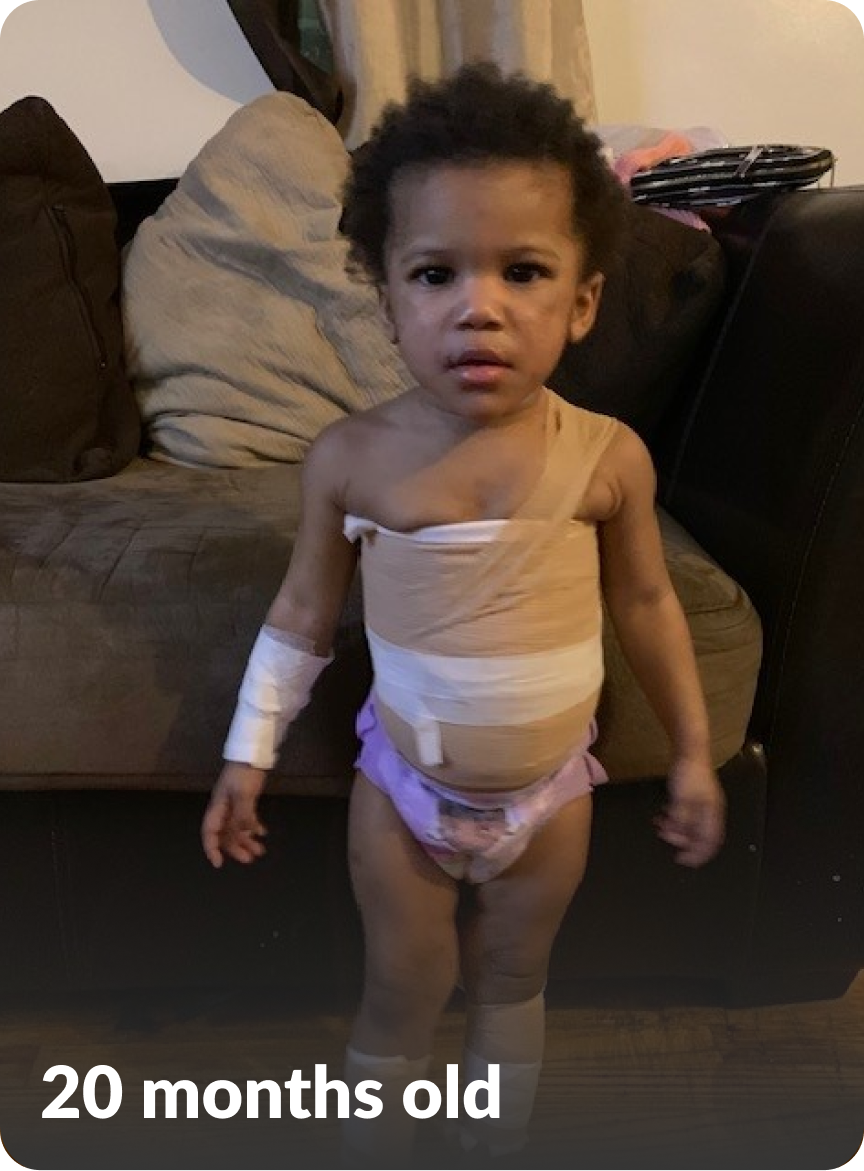
“It became a matter of just trying to keep her distracted from wanting to scratch.”
—Bailey’s mom
Constant itch, limited relief
- Intensely itchy lesions often emerged with exposure to sun, heat, and outdoor allergens
- Bailey’s parents had to split family activities when her sister wanted to go out
- Severe itch and lesions required frequent trips to the doctor
- Mom and Dad tried various treatments, from dietary changes to OTC creams and lotions to Rx topicals, but they provided only minimal relief

“With DUPIXENT, we don’t have to worry as much about her condition.”
—Bailey’s mom
Finding the control she was missing
- After seeing a pediatric dermatologist, Bailey started taking DUPIXENT
- With DUPIXENT, Bailey’s skin is clearer and she doesn’t itch nearly as much
- With less time thinking about her skin, Bailey’s family can now focus on the activities they do together
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia. The safety profile of DUPIXENT ± TCS in children followed through Week 52 was similar to the safety profile observed at Week 16 in AD-1652. The long-term safety profile of DUPIXENT ± TCS observed in children was consistent with that seen in adults and adolescents with atopic dermatitis.1
“Looking back on early pictures, her face looked so irritated.”
—Bailey’s mom
Signs and symptoms began in the first year of life
- Red, dry, patchy rashes on Bailey’s cheeks were first thought to be caused by the weather
- Intractable itching and oozing lesions spread to her scalp, arms, neck, and torso
- A diagnosis of severe AD was confirmed at 7 months of age
“It became a matter of just trying to keep her distracted from wanting to scratch.”
—Bailey’s mom
Constant itch, limited relief
- Intensely itchy lesions often emerged with exposure to sun, heat, and outdoor allergens
- Bailey’s parents had to split family activities when her sister wanted to go out
- Severe itch and lesions required frequent trips to the doctor
- Mom and Dad tried various treatments, from dietary changes to OTC creams and lotions to Rx topicals, but they provided only minimal relief
“With DUPIXENT, we don’t have to worry as much about her condition.”
—Bailey’s mom
Finding the control she was missing
- After seeing a pediatric dermatologist, Bailey started taking DUPIXENT
- With DUPIXENT, Bailey’s skin is clearer and she doesn’t itch nearly as much
- With less time thinking about her skin, Bailey’s family can now focus on the activities they do together
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia. The safety profile of DUPIXENT ± TCS in children followed through Week 52 was similar to the safety profile observed at Week 16 in AD-1652. The long-term safety profile of DUPIXENT ± TCS observed in children was consistent with that seen in adults and adolescents with atopic dermatitis.1
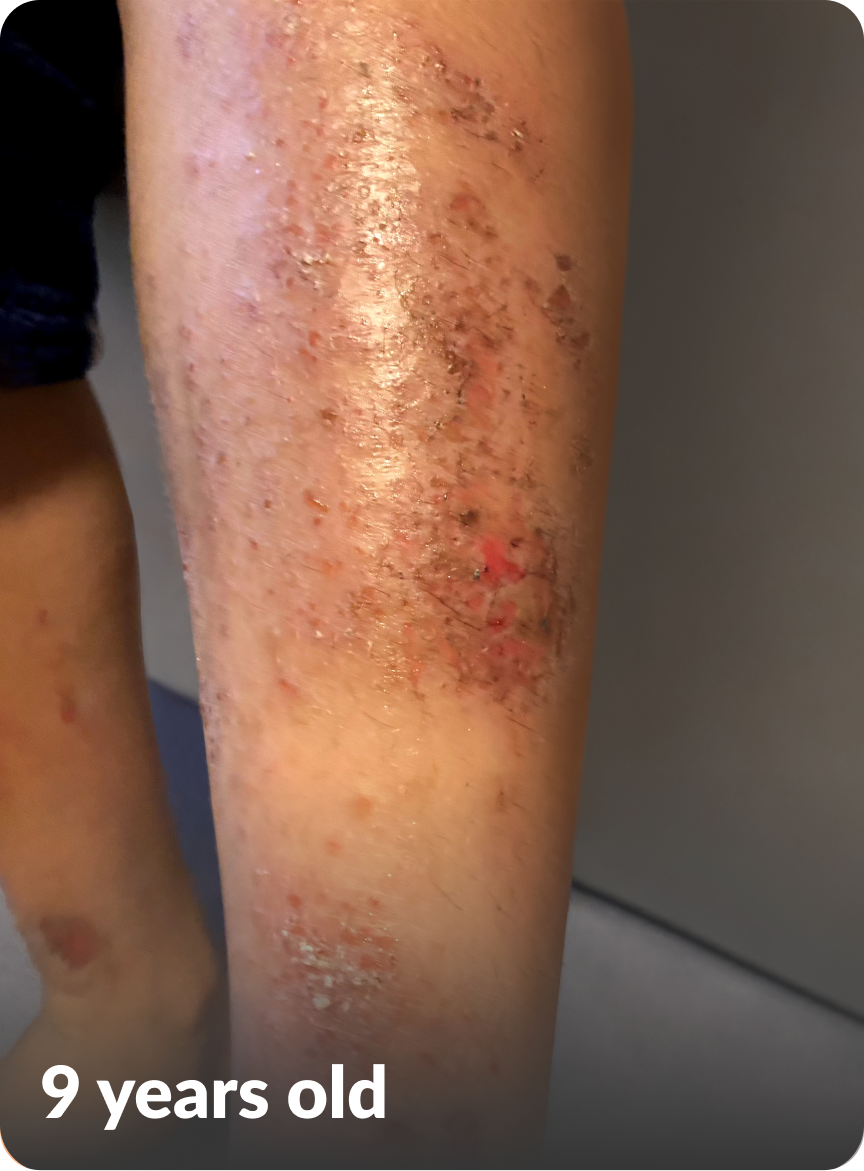
“His skin was so raw, everything he touched would bring tears to his eyes.”
—Kayden’s mom
A childhood marked by flare after flare
- Severe “cradle cap” appeared at 6 months, which HCP believed would resolve with time
- By age 2, Kayden’s rash spread to other locations, mostly face, legs, and torso
- By age 6, new flares appeared almost every week, with short-lasting relief from TCS
- Frequent oozing, raw lesions would make swimming intolerable
- Itching was severe both day and night
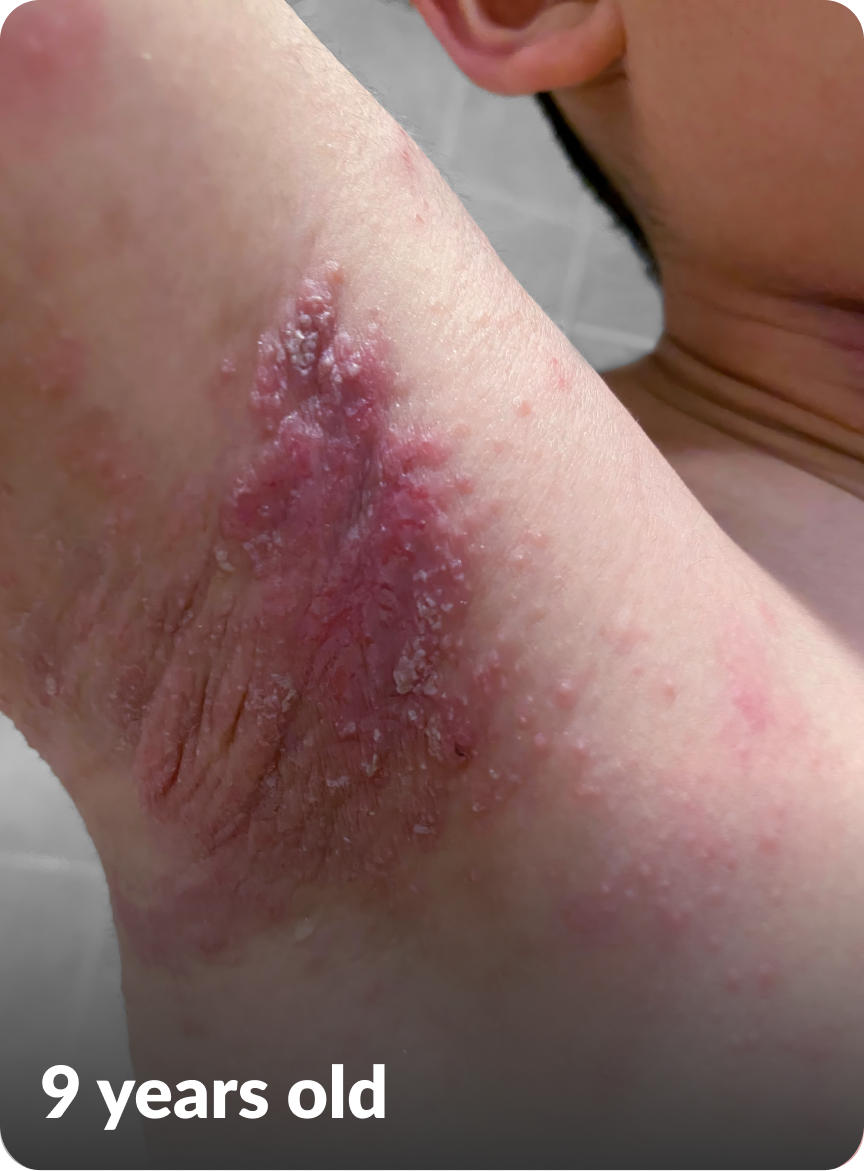
“I couldn’t bear seeing Kayden suffer any longer and started looking for other options.”
—Kayden’s mom
Multiple modalities, several HCPs, little relief
- After 7 years, Kayden was diagnosed with severe AD by a specialist
- Recommendations included topical Rx and OTC therapies, immunosuppressants
- Home treatments ranged from barrier moisturizers, oatmeal baths, and bleach baths to traditional Chinese medicine, teas, and baths
- Any relief of the painfully itchy rashes was short-lived

“With DUPIXENT, we’ve finally found something that really helps.”
—Kayden’s mom
Control after a decade of struggling
- After researching and talking with other parents and their HCP, Kayden’s parents agreed to DUPIXENT
- His lesions quickly showed signs of clearing, and by Week 16 his skin looked substantially clearer
- Kayden is much less bothered by itch, day and night
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia. The safety profile in adolescents through Week 16 was similar to that of adults with atopic dermatitis. In an open-label extension study, the long-term safety profile of DUPIXENT in adolescents observed through Week 52 was consistent with that seen in adults with atopic dermatitis.1
“His skin was so raw, everything he touched would bring tears to his eyes.”
—Kayden’s mom
A childhood marked by flare after flare
- Severe “cradle cap” appeared at 6 months, which HCP believed would resolve with time
- By age 2, Kayden’s rash spread to other locations, mostly face, legs, and torso
- By age 6, new flares appeared almost every week, with short-lasting relief from TCS
- Frequent oozing, raw lesions would make swimming intolerable
- Itching was severe both day and night
“I couldn’t bear seeing Kayden suffer any longer and started looking for other options.”
—Kayden’s mom
Multiple modalities, several HCPs, little relief
- After 7 years, Kayden was diagnosed with severe AD by a specialist
- Recommendations included topical Rx and OTC therapies, immunosuppressants
- Home treatments ranged from barrier moisturizers, oatmeal baths, and bleach baths to traditional Chinese medicine, teas, and baths
- Any relief of the painfully itchy rashes was short-lived
“With DUPIXENT, we’ve finally found something that really helps.”
—Kayden’s mom
Control after a decade of struggling
- After researching and talking with other parents and their HCP, Kayden’s parents agreed to DUPIXENT
- His lesions quickly showed signs of clearing, and by Week 16 his skin looked substantially clearer
- Kayden is much less bothered by itch, day and night
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia. The safety profile in adolescents through Week 16 was similar to that of adults with atopic dermatitis. In an open-label extension study, the long-term safety profile of DUPIXENT in adolescents observed through Week 52 was consistent with that seen in adults with atopic dermatitis.1
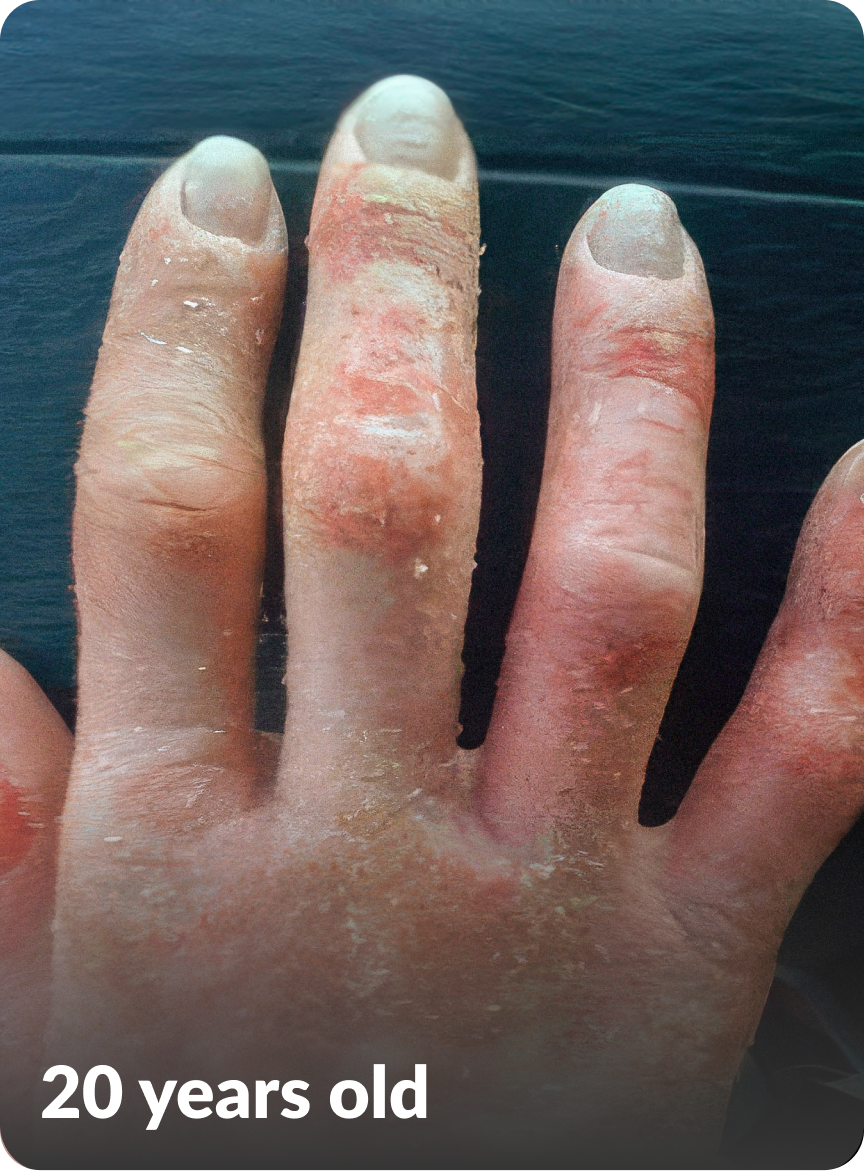
“The pediatrician reassured my mother that this was a common condition and that I’d outgrow it, but I never did...”
—Jennifer
When childhood AD extends into adulthood
- At 6 months of age, Jennifer presented with red, scaly skin on her elbows, knees, and cheeks and was diagnosed with severe AD
- Throughout her early childhood, she was often uncomfortable and irritated due to near constant itching
- Jennifer’s disease progressed as her itch persisted and her skin began to crack, peel, and ooze

“When my skin was at its worst, washing my hands and showering were both uncomfortable.”
—Jennifer
Running out of options
- She tried an elimination diet to see if certain foods were the cause of her signs and symptoms; unfortunately, nothing seemed to provide relief
- ≈90% of her body was covered with lesions and/or problem areas
- She was initially prescribed oral corticosteroids, but the relief didn’t last
- She cycled through several topical Rxs along with UV light therapy, bleach baths, and wet wraps—but nothing worked

“I’m actually in pictures these days—not just the one behind the camera.”
—Jennifer
Achieving change with DUPIXENT
- Over 3 decades after her initial diagnosis, Jennifer met with a specialist and began taking DUPIXENT in 2017
- Two weeks after starting treatment, she began noticing small changes in her signs and symptoms
- Her skin was clearer, and she noticed that she wasn't itching herself nearly as often or as aggressively
- For the first time in a long time, Jennifer feels like she has found something that actually works for her
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia.1
“The pediatrician reassured my mother that this was a common condition and that I’d outgrow it, but I never did...”
—Jennifer
When childhood AD extends into adulthood
- At 6 months of age, Jennifer presented with red, scaly skin on her elbows, knees, and cheeks and was diagnosed with severe AD
- Throughout her early childhood, she was often uncomfortable and irritated due to near constant itching
- Jennifer’s disease progressed as her itch persisted and her skin began to crack, peel, and ooze
“When my skin was at its worst, washing my hands and showering were both uncomfortable.”
—Jennifer
Running out of options
- She tried an elimination diet to see if certain foods were the cause of her signs and symptoms; unfortunately, nothing seemed to provide relief
- ≈90% of her body was covered with lesions and/or problem areas
- She was initially prescribed oral corticosteroids, but the relief didn’t last
- She cycled through several topical Rxs along with UV light therapy, bleach baths, and wet wraps—but nothing worked
“I’m actually in pictures these days—not just the one behind the camera.”
—Jennifer
Achieving change with DUPIXENT
- Over 3 decades after her initial diagnosis, Jennifer met with a specialist and began taking DUPIXENT in 2017
- Two weeks after starting treatment, she began noticing small changes in her signs and symptoms
- Her skin was clearer, and she noticed that she wasn't itching herself nearly as often or as aggressively
- For the first time in a long time, Jennifer feels like she has found something that actually works for her
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia.1

“As an adult, I would sometimes wear gloves to shield and protect my hands from bright direct sunlight.”
—Cat
Itching and scratching defined Cat’s childhood
- Symptoms included extreme itch on arms and legs, sensation of skin burning, fluid-filled blisters, swelling, and cracking skin
- Diagnosed with moderate AD at age 4; severe AD as an adult
- By age 13, the flares had improved but did not resolve entirely

“I hit a point in my life where I just accepted this was going to be the normal course for my hands. Then I saw a commercial for DUPIXENT, and I remember immediately feeling hope.”
—Cat
So many topical treatments, so little help
- The condition of Cat’s hands impacted her as a nursing student and professional cheerleader
- In college, Cat received steroid injections and antibiotics for infections from scratching; in her early twenties, a dermatologist prescribed a higher potency Rx topical
- Some treatments would calm the itch for a while, but the skin became paper-thin

“Since starting DUPIXENT, my main priority is not around atopic dermatitis.”
—Cat
Finding the control she was missing
- Cat initiated the discussion about DUPIXENT with her dermatologist
- Once Cat started DUPIXENT, she began noticing improvements in her skin
- Cat is currently on DUPIXENT, which has provided more control
- After decades of suffering, Cat’s disease is finally under control
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia.1
“As an adult, I would sometimes wear gloves to shield and protect my hands from bright direct sunlight.”
—Cat
Itching and scratching defined Cat’s childhood
- Symptoms included extreme itch on arms and legs, sensation of skin burning, fluid-filled blisters, swelling, and cracking skin
- Diagnosed with moderate AD at age 4; severe AD as an adult
- By age 13, the flares had improved but did not resolve entirely
“I hit a point in my life where I just accepted this was going to be the normal course for my hands. Then I saw a commercial for DUPIXENT, and I remember immediately feeling hope.”
—Cat
So many topical treatments, so little help
- The condition of Cat’s hands impacted her as a nursing student and professional cheerleader
- In college, Cat received steroid injections and antibiotics for infections from scratching; in her early twenties, a dermatologist prescribed a higher potency Rx topical
- Some treatments would calm the itch for a while, but the skin became paper-thin
“Since starting DUPIXENT, my main priority is not around atopic dermatitis.”
—Cat
Finding the control she was missing
- Cat initiated the discussion about DUPIXENT with her dermatologist
- Once Cat started DUPIXENT, she began noticing improvements in her skin
- Cat is currently on DUPIXENT, which has provided more control
- After decades of suffering, Cat’s disease is finally under control
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia.1

“On camping trips, the whole family would get involved in my eczema journey, helping apply the treatment. So embarrassing.”
—Paulo
Rashes appeared when Paulo was only an infant
- When OTC treatments and creams didn’t work well enough, parents took Paulo to see a pediatrician
- Initial diagnosis was baby eczema; signs and symptoms included lesions all over their body
- Officially diagnosed with moderate AD at 6 years old

“Although I loved traveling, I was always preoccupied with all the scratching and picking at my skin. I felt I had tried every oral and topical Rx possible; I was desperate for something different.”
—Paulo
Coping involved avoiding
- Swimming, jacuzzis, and hot, cold, or dry climates exacerbated symptoms; also experienced sensitivities to fragrances, fabrics, and temperature changes
- As a professional dancer, dance-wear caused skin irritation. Paulo’s skin would also flake off during performances
- Paulo asked for other treatments—doctors would prescribe different topical Rxs, but the disease remained uncontrolled
- Signs and symptoms included itching, flaky skin, and more
- Made frequent trips to urgent care

“After 2 decades of battling eczema, I now have a treatment where my skin is clearer and I’m less itchy.”
—Paulo
Years later, a way forward
- Paulo had already heard about DUPIXENT when their new dermatologist brought it up
- With DUPIXENT, Paulo began noticing less itch as well as improvements in skin
- Less worried about how different climates might trigger a flare
- With continued treatment, Paulo's moderate AD is now under control
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia.1
“On camping trips, the whole family would get involved in my eczema journey, helping apply the treatment. So embarrassing.”
—Paulo
Rashes appeared when Paulo was only an infant
- When OTC treatments and creams didn’t work well enough, parents took Paulo to see a pediatrician
- Initial diagnosis was baby eczema; signs and symptoms included lesions all over their body
- Officially diagnosed with moderate AD at 6 years old
“Although I loved traveling, I was always preoccupied with all the scratching and picking at my skin. I felt I had tried every oral and topical Rx possible; I was desperate for something different.”
—Paulo
Coping involved avoiding
- Swimming, jacuzzis, and hot, cold, or dry climates exacerbated symptoms; also experienced sensitivities to fragrances, fabrics, and temperature changes
- As a professional dancer, dance-wear caused skin irritation. Paulo’s skin would also flake off during performances
- Paulo asked for other treatments—doctors would prescribe different topical Rxs, but the disease remained uncontrolled
- Signs and symptoms included itching, flaky skin, and more
- Made frequent trips to urgent care
“After 2 decades of battling eczema, I now have a treatment where my skin is clearer and I’m less itchy.”
—Paulo
Years later, a way forward
- Paulo had already heard about DUPIXENT when their new dermatologist brought it up
- With DUPIXENT, Paulo began noticing less itch as well as improvements in skin
- Less worried about how different climates might trigger a flare
- With continued treatment, Paulo's moderate AD is now under control
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus, other herpes simplex virus infection, dry eye, and eosinophilia.1
Clinical Trial Designs and Results
162 infants to preschoolers (6 months to 5 years) in AD-1539 (16 weeks) with moderate-to-severe atopic dermatitis inadequately controlled with topical prescription therapies were randomized to DUPIXENT + TCS or placebo + TCS. Patients 15 kg but >30 kg received 300 mg Q4W. Patients 5 kg but <15 kg received 200 mg Q4W. Patients had an IGA score ≥3 on a scale of 0 to 4, an EASI score ≥16 on a scale of 0 to 72, and BSA involvement of ≥10%. At baseline, 23% of infants to preschoolers had an IGA score of 3 (moderate), 77% had an IGA of 4 (severe), mean EASI score was 34.1, and weekly average of daily Worst Scratch/Itch NRS was 7.6 on a scale of 0 to 10.1,2
The primary endpoint was the proportion of subjects with an IGA 0 (clear) or 1 (almost clear) at Week 16 (28% of patients treated with DUPIXENT + TCS vs 4% with placebo + TCS, P<0.0001). Other endpoints included the proportion of subjects with EASI-75 at Week 16 (53% of patients treated with DUPIXENT + TCS vs 11% with placebo + TCS, P<0.0001) and ≥4-point improvement in the Worst Scratch/Itch NRS at Week 16 (48% of patients treated with DUPIXENT + TCS vs 9% with placebo + TCS, P<0.0001).1,2
367 children (6-11 years) in AD-1652 (16 weeks) with severe atopic dermatitis inadequately controlled with topical prescription therapies were randomized to DUPIXENT + TCS or placebo + TCS. Patients ≥30 kg but <60 kg received 200 mg Q2W after a 400 mg loading dose. Patients 15 kg but <30 kg received 300 mg Q4W after a 600 mg loading dose. Patients had an IGA score of 4, an EASI score ≥21, and BSA involvement ≥15%. Mean EASI score was 37.9 and weekly averaged Peak Pruritus NRS was 7.8 on a scale of 0 to 10.1
The primary endpoint was the proportion of subjects with an IGA 0 (clear) or 1 (almost clear) at Week 16 (39% of patients ≥30 kg treated with DUPIXENT + TCS vs 10% with placebo + TCS, and 30% of patients <30 kg treated with DUPIXENT + TCS vs 13% with placebo + TCS). Other endpoints included the proportion of subjects with EASI-75 at Week 16 (75% of patients ≥30 kg treated with DUPIXENT + TCS vs 26% with placebo + TCS, and 75% of patients <30 kg treated with DUPIXENT + TCS vs 28% with placebo + TCS) and ≥4-point improvement in the Peak Pruritus NRS at Week 16 (61% of patients ≥30 kg treated with DUPIXENT + TCS vs 13% with placebo + TCS, and 54% of patients <30 kg treated with DUPIXENT + TCS vs 12% with placebo + TCS).1,3
251 adolescents (12-17 years) in AD-1526 (16 weeks) with moderate-to-severe atopic dermatitis inadequately controlled with topical prescription therapies were randomized to DUPIXENT or placebo. Adolescents ≥60 kg received DUPIXENT 300 mg Q2W after a 600 mg loading dose, and adolescents <60 kg received 200 mg Q2W after a 400 mg loading dose. Patients had an IGA score ≥3 on a scale of 0 to 4, an EASI score ≥16 on a scale of 0 to 72, and BSA involvement of ≥10%. At baseline, 46% had an IGA score of 3 (moderate), 54% had an IGA of 4 (severe), mean EASI score was 36, and weekly averaged Peak Pruritus NRS was 8 on a scale of 0 to 10.1
The primary endpoint was the proportion of subjects with an IGA 0 (clear) or 1 (almost clear) and ≥2-point improvement at Week 16 (24% of patients treated with DUPIXENT vs 2% with placebo, P<0.001). Other endpoints included the proportion of subjects with EASI-75 at Week 16 (42% of patients treated with DUPIXENT vs 8% with placebo, P<0.001) and ≥4-point improvement in the Peak Pruritus NRS at Week 16 (37% of patients treated with DUPIXENT vs 5% with placebo, P<0.001).1,4
917 adults in SOLO 1 and SOLO 2 (16 weeks each) and 421 adults in CHRONOS (52 weeks) with moderate-to-severe atopic dermatitis inadequately controlled with topical prescription therapies were randomized to DUPIXENT or placebo. All patients in CHRONOS were treated with concomitant TCS. All patients who received DUPIXENT were given 300 mg Q2W after a 600 mg loading dose. Patients had an IGA score ≥3 on a scale of 0 to 4, an EASI score ≥16 on a scale of 0 to 72, and BSA involvement of ≥10%. At baseline, 52% had an IGA score of 3 (moderate), 48% had an IGA of 4 (severe), mean EASI score was 33, and weekly averaged Peak Pruritus NRS was 7 on a scale of 0 to 10.1
The primary endpoint was the proportion of subjects with an IGA 0 (clear) or 1 (almost clear) and ≥2-point improvement at Week 16 (38% and 36% of patients treated with DUPIXENT vs 10% and 9% with placebo in SOLO 1 and SOLO 2, respectively, P<0.001; 39% of patients treated with DUPIXENT + TCS vs 12% with placebo + TCS in CHRONOS, P<0.0001). Other endpoints included the proportion of subjects with EASI-75 at Week 16 (51% and 44% of patients treated with DUPIXENT vs 15% and 12% with placebo in SOLO 1 and SOLO 2, respectively, P<0.001; 69% of patients treated with DUPIXENT + TCS vs 23% with placebo + TCS in CHRONOS, P<0.0001) and ≥4-point improvement in the Peak Pruritus NRS at Week 16 (41% and 36% of patients treated with DUPIXENT vs 12% and 10% with placebo in SOLO 1 and SOLO 2, respectively, P<0.001; 59% of patients treated with DUPIXENT + TCS vs 20% with placebo + TCS in CHRONOS, P<0.0001).1,5,6
Watch healthcare providers discuss patient concerns and how they managed them
AD, atopic dermatitis; BSA, body surface area; EASI, Eczema Area and Severity Index; IGA, Investigator’s Global Assessment; NRS, numerical rating scale; OTC, over the counter; Q2W, once every 2 weeks; Q4W, once every 4 weeks; TCS, topical corticosteroids.