Need more information? Contact a rep now
DUPIXENT Overview
DUPIXENT is indicated for adult and pediatric patients aged 6 months and older with moderate-to-severe AD whose disease is not adequately controlled with topical prescription therapies or when those therapies are not advisable. DUPIXENT can be used with or without topical corticosteroids.1
It has been 9 years since initial FDA approval of DUPIXENT in AD in adults.1,a DUPIXENT has more than 1.5 million patients on therapy across approved indications worldwide.2,b
Approved DUPIXENT indications with links for more information:
- Moderate-to-severe atopic dermatitis (6+ months of age)
- Moderate-to-severe asthma (6+ years of age)
- Chronic rhinosinusitis with nasal polyps (12+ years of age)
- Eosinophilic esophagitis (1+ year of age)
- Prurigo nodularis (18+ years of age)
- Chronic obstructive pulmonary disease (18+ years of age)
- Chronic spontaneous urticaria (2+ years of age)
- Bullous pemphigoid (18+ years of age)
- Allergic fungal rhinosinusitis (6+ years of age)
aFDA approved since 2017 for adults, 2019 for adolescents (aged 12-17 years), 2020 for children (aged 6-11 years), and 2022 for infants to preschoolers (aged 6 months to 5 years) with uncontrolled moderate-to-severe AD.
bThe worldwide patient number is largely comprised of patients treated with DUPIXENT from 11 countries (Brazil, Canada, China, France, Germany, Italy, Japan, the Netherlands, Spain, UK, and US) and the rest of the world comprising ≈12% of this worldwide patient number. This number is composed of the following US approved indications: AD, asthma, BP, COPD, CRSwNP, CSU, PN, and EoE. Data through March 2026.
There is a strong recommendation for the use of DUPIXENT in3,4,a:
- American Academy of Dermatology (AAD) Atopic Dermatitis Guidelines
- American Academy of Allergy, Asthma, and Immunology (AAAAI)/American College of Allergy, Asthma, and Immunology (ACAAI) Joint Task Force Atopic Dermatitis Guidelines
aInclusion in AAD and AAAAI/ACAAI AD Guidelines does not denote endorsement or recommendation of product use by AAD and AAAAI/ACAAI.
DUPIXENT Efficacy
Significant itch reduction was demonstrated at Week 16 with DUPIXENT in SOLO 1 and SOLO 2 (secondary endpoint), two phase 3, placebo-controlled, monotherapy pivotal trials.1,5
- 41% of adults treated with DUPIXENT (n=213) achieved ≥4-point reduction in Peak Pruritus NRS (itch) vs 12% with placebo in SOLO 1 (n=212; P<0.001)
- 36% of adults treated with DUPIXENT (n=225) achieved ≥4-point reduction in Peak Pruritus NRS (itch) vs 10% with placebo at Week 16 in SOLO 2 (n=221; P<0.001)
Itch was also assessed through 1 year in a trial of DUPIXENT + TCS vs placebo + TCS.1,6
In a post hoc pooled analysis of SOLO 1 and SOLO 2, decrease in daily peak pruritus NRS from baseline in adults starting at Day 2 with DUPIXENT monotherapy7
- Change in daily Peak Pruritus NRS from baseline in a post hoc analysis of pooled SOLO 1 and SOLO 2 trials (-4.5% with DUPIXENT [n=457] vs -0.6% with placebo [n=460])
Definitive conclusions cannot be made about Day 2 results as this was a post hoc analysis in which data were not multiplicity controlled and P value was nominal.
See more itch results in adults
See more itch data across other AD patient populations
Based on the results of CHRONOS, a phase 3, placebo-controlled pivotal trial that evaluated DUPIXENT + TCS in adults with moderate-to-severe AD, patients achieved sustained skin clearance at Week 521,6:
- 36% of DUPIXENT-treated patients achieved clear or almost-clear skin (IGA 0 or 1 and ≥2-point improvement) vs 13% with placebo + TCS (P<0.0001; secondary endpoint)
See adult skin clearance data
See more skin clearance data across other AD patient populations
Each patient may respond differently to DUPIXENT. Use clinical judgment to determine how long a patient should remain on DUPIXENT.
In DUPIXENT pivotal clinical trials in AD, itch was measured using a 0- to 10-point numerical rating scale (NRS) assessing a patient’s worst itch over the previous 24 hours.
To calculate8:
- Peak Pruritus NRS asks patients who can self-report (6+ years of age): "On a scale of 0 to 10, how would you rate your itch overall (on average) during the previous 24 hours?"
- Worst Scratch/Itch NRS asks caregivers of children aged 6 months to 5 years: "On a scale of 0 to 10, how would you rate the scratching/itching of the child you are a caregiver for at its worst during the previous 24 hours?"
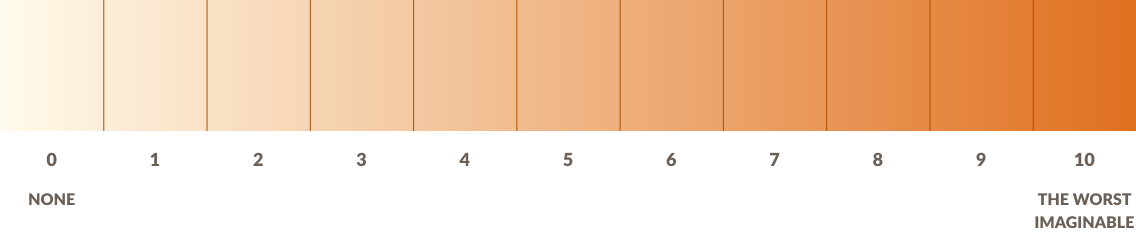
A reduction of ≥4 points from baseline is a clinically meaningful change.1
The Eczema Area and Severity Index (EASI) combines the severity of eczema signs and the extent of skin involvement to measure lesional signs of AD.9
The severity of each of 4 eczema signs is assessed on a scale of 0 to 39
- The signs of eczema (erythema, edema/papulation, excoriation, and lichenification) are graded using a defined process by the extent to which the patient is affected
The extent of lesions in each body region is evaluated9
- The extent of lesions in each body region is evaluated based on the percentage of involvement and is given a value between 0 and 6
- Each body region value is then weighted by a corresponding multiplier; lower extremities are weighted more while head and neck are weighted the least
Each region gets a total region score9:
Severity Score x Area Score x Multiplier = Region Score
The final EASI score is the sum of all 4 region scores. The composite score, on a scale from 0 to 72, determines the severity of the signs of eczema and the extent to which the patient is affected.9,a
An improvement of at least 75% in lesion extent and severity (EASI-75) from baseline is a clinically meaningful change.1
aIn patients <8 years of age, the multipliers for the head and neck are 0.2, the trunk is 0.3, the upper extremities are 0.2, and the lower extremities are 0.3. In patients ≥8 years of age, the multipliers for the head and neck are 0.1, the trunk is 0.3, the upper extremities are 0.2, and the lower extremities are 0.4.9
Investigator's Global Assessment (IGA) for skin clearance assesses the overall severity of clinical signs of atopic dermatitis using a 0- to 4-point scoring system.2
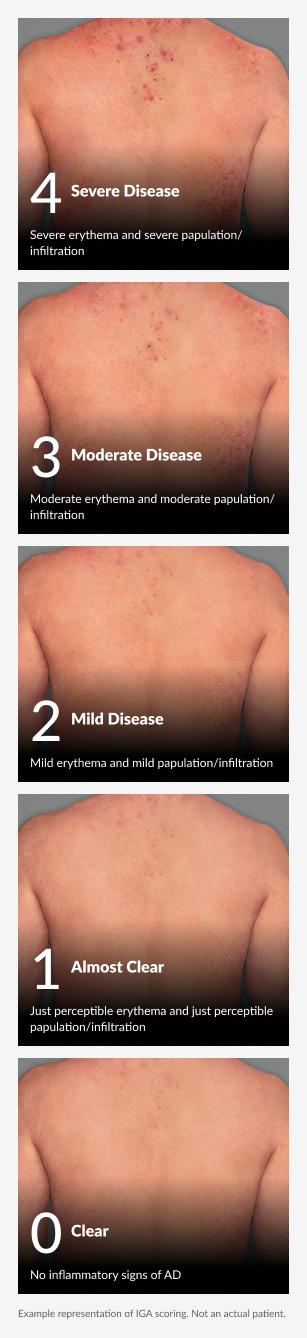
A clinical responder was defined as a patient achieving IGA 0 or 1 and, in adults and adolescents, ≥2-point improvement from baseline.1
DUPIXENT Safety Profile
The most common adverse reactions (incidence ≥1%) in patients with atopic dermatitis are injection site reactions, conjunctivitis, blepharitis, oral herpes, keratitis, eye pruritus (itch), other herpes simplex virus infection, dry eye, and eosinophilia. The safety profile of DUPIXENT in pediatric patients 6 months to 17 years of age through Week 16 was similar to the safety profile from studies in adults with AD. In an open-label extension study (AD-1434), the safety profile of DUPIXENT ± TCS in pediatric patients observed through Week 52 was consistent with that seen in adults with AD. In AD-1434, hand-foot-and-mouth disease and skin papilloma (incidence ≥2%) were reported in patients 6 months to 5 years of age. These cases did not lead to study drug discontinuation.1
See more information on DUPIXENT safety
DUPIXENT has a demonstrated long-term safety profile, including patients as young as 6 months of age, that’s supported by clinical data. The safety profile of DUPIXENT through Week 16 (in pivotal trials) and Week 52 (in an open-label extension trial, AD-1434) observed in pediatric patients aged 6 months to 17 years was consistent with that seen in adults with AD. In AD-1434, hand-foot-and-mouth disease and skin papilloma (incidence ≥2%) were reported in patients 6 months to 5 years of age. These cases did not lead to study drug discontinuation.1
See more information on DUPIXENT safety
Other Attributes/Considerations
Consider completing all age-appropriate vaccinations as recommended by current immunization guidelines prior to initiating treatment with DUPIXENT. Avoid use of live vaccines during treatment with DUPIXENT.1
DUPIXENT does not have a boxed warning.1
Select Important Safety Information: Warnings and Precautions—Hypersensitivity: Hypersensitivity reactions, including anaphylaxis, acute generalized exanthematous pustulosis (AGEP), serum sickness or serum sickness-like reactions, angioedema, generalized urticaria, rash, erythema nodosum, and erythema multiforme have been reported. A case of AGEP was reported in an adult subject who participated in the bullous pemphigoid development program. If a clinically significant hypersensitivity reaction occurs, institute appropriate therapy and discontinue DUPIXENT.
Please see additional Warnings and Precautions in the Prescribing Information and Important Safety Information below.
No. No initial lab testing or ongoing lab monitoring is required with DUPIXENT, according to the Prescribing Information.1
No. DUPIXENT is not an immunosuppressant.1
DUPIXENT Real-world Data
Yes, skin improvement was assessed through 4 years in a retrospective, multicenter, Italian dynamic cohort study of adults with moderate-to-severe AD.10
See skin improvement data at 4 years
Yes, itch response was assessed through 3 years in patients aged 12+ years with moderate-to-severe AD in PROSE, an ongoing longitudinal, prospective, observational registry in the US and Canada.11,12
See itch data at 3 years
Persistency was reported in 2 real-world-studies:
- 5-years of RELIEVE-AD data with patients 18+ years 2,13
- Real-world healthcare claims from IBM MarketScan Commercial and Medicare supplemental databases14
See persistency data up to 5 years
Patient satisfaction was reported in RELIEVE-AD, a single-arm, prospective, observational study. Patients with moderate-to-severe AD enrolled in DUPIXENT MyWay® prior to initiating treatment with DUPIXENT. Patients completed multiple surveys over 72 months. At Month 72, participants that responded to the survey at Month 33 and/or Month 48 were recontacted for Month 72 follow-up.15
See satisfaction data through 6 years
Prescribing DUPIXENT
DUPIXENT offers at-home and in-office administration options. DUPIXENT is administered as a subcutaneous injection twice a month or monthly (depending on age and weight) after an initial loading dose (in patients aged 6+ years). In patients aged 6 months to 5 years, no initial loading dose is recommended.1
DUPIXENT has one dosing regimen in adults and weight-tired dosing in pediatric populations (ages 6 months to 17 years)1:
One dosage regimen in adults regardless of weight
- 600 mg loading dose (2 × 300 mg SC injections), then 300 mg (1 SC injection) every 2 weeks
Weight-tiered dosing in children and adolescents (6-17 years)
- ≥60 kg: 600 mg loading dose (2 × 300 mg SC injections), then 300 mg (1 SC injection) every 2 weeks
- 30 kg to <60 kg: 400 mg loading dose (2 × 200 mg SC injections), then 200 mg (1 SC injection) every 2 weeks
- 15 kg to <30 kg: 600 mg loading dose (2 × 300 mg SC injections), then 300 mg (1 SC injection) every 4 weeks
Weight-tiered dosing in infants to preschoolers (6 months to 5 years)
- 15 kg to <30 kg: 300 mg (1 SC injection) every 4 weeks (no initial loading dose is recommended)
- 5 kg to <15 kg: 200 mg (1 SC injection) every 4 weeks (no initial loading dose is recommended)
See the full dosing schedule
No, the use of topical corticosteroids (TCS) or topical calcineurin inhibitors (TCI) is not required with DUPIXENT.
- DUPIXENT can be used with or without TCS1
- DUPIXENT can be used concomitantly with TCIs, but should be reserved for problem areas only, such as the face, neck, and intertriginous and genital areas1
Access and Support
To help patients better understand DUPIXENT and feel confident taking a biologic for AD, you can direct them to patient-friendly education and support resources available at DUPIXENT.com, which help explain biologic therapy, set expectations, and support patients throughout treatment.
Key resources include
- Educational content on how DUPIXENT works and how it differs from traditional systemic therapies
- Step-by-step supplemental injection training videos and instructions to support at-home administration
- Patient stories and testimonials from other patients taking DUPIXENT
- Treatment journey and FAQ sections that address common questions about safety, dosing, and cost
- The DUPIXENT MyWay® program, which offers nurse support, financial assistance information, and ongoing patient guidance
DUPIXENT has the #1 best access among specialty systemic therapies indicated for AD.2,a,b
- ≈96% of commercial patients (6+ months of age) nationally are covered for DUPIXENT
- ≈89% of commercial patient lives have to fail only 1 or 2 prescription topical treatments
aMMIT Analysis, May 2026. Analysis included DUPIXENT, tralokinumab, upadacitinib, abrocitinib, lebrikizumab, and nemolizumab.
bBased on available published commercial UM coverage criteria.
The amount your patients pay for DUPIXENT will largely depend on whether they have insurance, the type of insurance they have, whether their insurance provider considers the medication to be preferred or not preferred, and whether they’ve met their deductible.
A great place to start is with DUPIXENT MyWay®, a patient support program that can help enable access to DUPIXENT and offers financial assistance to eligible patients, one-on-one nursing support, and more.
The DUPIXENT MyWay® Interim Access Program assists eligible, commercially insured patients who previously started DUPIXENT and are experiencing a specific, short-term lapse in therapy. It temporarily provides eligible patients DUPIXENT at no cost, subject to program terms and conditions. You or your patients can contact DUPIXENT MyWay at to learn more.
You can use this guide to find out about the prior authorization request and appeal process for your patients appropriate for DUPIXENT.
AD, atopic dermatitis; BP, bullous pemphigoid; COPD, chronic obstructive pulmonary disease; CRSwNP, chronic rhinosinusitis with nasal polyps; CSU, chronic spontaneous urticaria; EASI, Eczema Area and Severity Index; EoE, eosinophilic esophagitis; IGA, Investigator’s Global Assessment; NRS, numerical rating scale; OTC, over the counter; PN, prurigo nodularis; Q2W, once every 2 weeks; Q4W, once every 4 weeks; SC, subcutaneous.